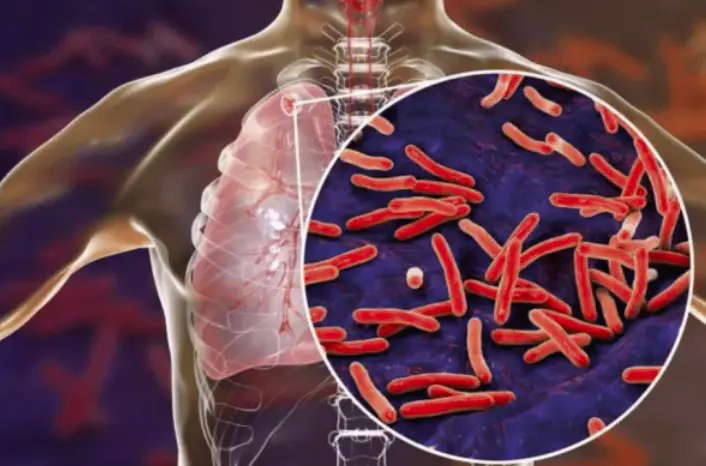
CAPE TOWN, SOUTH AFRICA — Citizens seeking private tb care in south africa face a heavily fragmented medical pathway characterized by severe pharmaceutical supply shortages and patchy integration with public health surveillance systems.While tuberculosis claims approximately 50,000 lives nationwide each year, patients who first consult private general practitioners or local pharmacies frequently encounter delayed diagnostic testing and uncoordinated treatment protocols.
Although over 90 percent of diagnosed patients present with drug-susceptible tuberculosis—requiring a standardized six-month regimen of four baseline antibiotics—private sector access to continuous pharmaceutical stock remains remarkably limited, increasing the risk of treatment interruption and drug resistance.
Sector Distribution and Private TB Care in South Africa
Data compiled from national prevalence surveys and clinical research projects highlights patient care-seeking behaviors across public and private health tiers:
Clinical Parameter Category
National Metric & Sector Distribution Data
Annual Tuberculosis Mortality
~50,000 deaths annually across South Africa
Initial Private Care Seeking
8.1% to 29% of patients first consult private doctors or pharmacies
Drug-Susceptible Standard Regimen
4 drugs for 2 months, followed by 2 drugs for 4 months
Drug-Resistant Protocol Scope
3 to 7 specialized drugs over 6 to 24 continuous months
Technical Mechanics of Supply Shortages facing private tb care in south africa
Understanding the operational barriers impeding private tb care in south africa underscores why private sector integration remains challenging:
Commercial Supply Chain Disincentives: Due to minimal commercial demand in retail pharmaceutical networks, most community pharmacies do not carry essential first-line anti-TB medicines.
Absence of Dedicated Medical Scheme Networks: Major private health insurers, including Discovery Health, do not maintain designated specialist practitioner networks dedicated exclusively to managing tuberculosis.
Delayed Referral Chains and Loss to Follow-Up: Patients moving between unlinked private clinics and public diagnostic centers frequently experience diagnostic delays, enabling active lung transmission to continue unchecked.
Public-Private Diagnostic Integration and Digital Triage
To address diagnostic fragmentation, pilot programs are testing digital linkage solutions between private general practitioners and public laboratory networks.A regional pilot in KwaZulu-Natal connected 158 private doctors to free public laboratory testing using the Vula smartphone application.Participating physicians submitted sputum samples that successfully identified 107 confirmed cases, demonstrating the viability of shared diagnostic infrastructure.
Clinical experts, including Prof. Keertan Dheda of Groote Schuur Hospital, argue that expanding public-private partnerships is necessary. Designating specific community pharmacies to stock publicly funded TB medications and training retail pharmacists to perform rapid symptom screening and digital referrals can significantly shorten diagnostic timelines.
Treatment Adherence, Drug Resistance, and Regional Policy Lessons
Completing the full six-month course of antibiotic therapy remains the single most critical factor in curing tuberculosis and preventing relapse.Premature treatment cessation—often triggered when clinical symptoms temporarily improve—serves as the primary driver of multidrug-resistant tuberculosis (MDR-TB), which requires up to two years of complex, high-cost toxic therapy.
These structural care gaps offer crucial policy lessons for other high-burden African nations, such as Nigeria, where patent medicine vendors and community pharmacies serve as the primary point of contact for individuals experiencing chronic coughs.Establishing seamless referral mechanisms between private primary care providers, retail pharmacies, and public health infrastructure remains essential to stopping community transmission and achieving global end-TB targets.
Why It Matters: Uncoordinated private TB care leads to delayed testing, incomplete treatment regimens, and drug resistance; linking private pharmacies and doctors to public diagnostics is vital to curbing community spread.
Antibiotic Overuse and Resistance: A Call to Action… Antibiotic overuse and resistance pose significant dangers to public health . Overuse refers to the unnecessary or excessive use of antibiotics, while resistance occurs when bacteria develop the ability to withstand the effects of antibiotics, rendering…
Nigerian Patients Left to Navigate Fragmented Care… ABUJA, NIGERIA — Public health stakeholders, government officials, and medical practitioners gathered at the 2026 Health Equity Conference in Abuja have warned that fragmented care in nigeria leaves vulnerable patients navigating disconnected hospitals, private laboratories,…
Tuberculosis Symptoms and Treatment: What You Need to Know Tuberculosis, or TB, is one of the oldest diseases known to humans, and it remains a major killer. Nigeria has one of the highest TB burdens in Africa, and many people with the disease have…
Plateau Estimates 11,000 TB Cases This Year as… JOS, NIGERIA — Health authorities in Plateau State estimate that approximately 11,000 people will contract tuberculosis in plateau state in 2026, as ongoing pharmaceutical supply chain disruptions and insecurity hinder disease containment across North-Central Nigeria.…